
Navigating the final chapters of life brings profound changes, not least of which are shifts in end of life eating habits. As individuals approach the end of their lives, it’s common to witness a natural decline in their desire for food and drink.
This phase, often distressing for loved ones and caregivers, is a normal part of the dying process. The body has a decreasing need for food and fluids and providing them can actually increase discomfort during the end of life.
Understanding these changes is important for providing compassionate care that respects the natural course of life’s end.
As a Registered Dietitian for over a decade and working with countless end of life patients, it’s important to educate caregivers and fellow Dietitian’s on how to discuss this topic. When you know what to expect it can help to feel more at peace during this time.
What is End of Life?
End of life or hospice refers to the final phase of an individual’s life. This is a time when medical treatments no longer contribute to recovery and life expectancy is less than 6 months.
This period is characterized by a shift in focus towards providing comfort care. The care goals are to ease symptoms and support the emotional, spiritual, and physical comfort of the individual and loved ones.
It involves pain management, addressing psychological and spiritual concerns, and offering support to families and caregivers.
The goal is to ensure dignity and quality of life for the person nearing the end of life, allowing them to live as fully and comfortably as possible in their remaining time.
End of life care does not mean end of care, it means a shift in care.
End of Life Stages Timeline
I won’t get too into the weeds about the end of life stages timeline, but as you can tell from the chart below that there are many nutrition indicators. Even those that are not directly nutrition, will affect food intake such as increased sleeping, nausea, and increased time in bed.
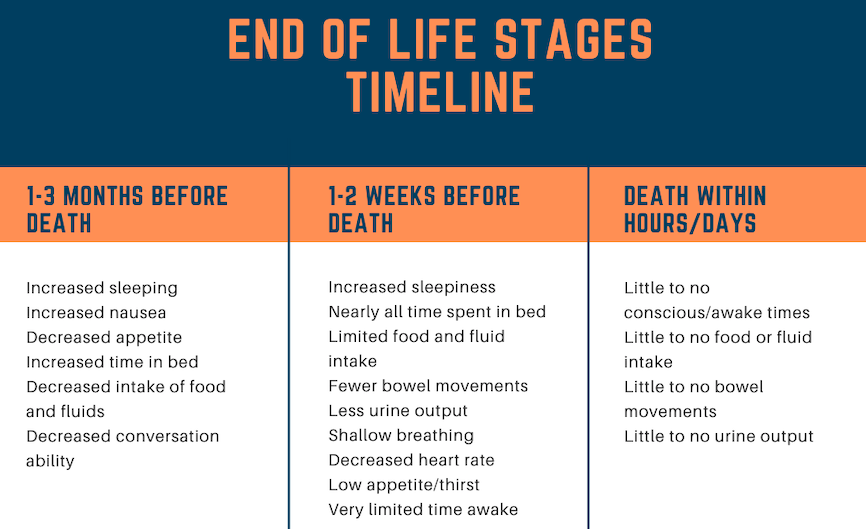
With so many nutrition indicators during the end of life stages and prior to, it’s important that Dietitian’s are heavily involved in the discussions. This can help to ease the emotional burden that loved ones may feel watching their loved ones intake go down.
If you’re a Dietitian and want to know more about how to initiate these discussions, I recommend reading: Comfort Feeding End of Life: A Dietitian’s Conversation.
End of Life Nutrition Symptoms
End of life triggers many changes in eating habits. As a Dietitian, I would say that nutrition changes are one of the most noticeable predictors that end of life is coming.
This makes the role of a Dietitian in end of life eating habits essential. Dietitians can help provide education and comfort as to what to expect in the coming 6 months or less. Knowing what is expected can provide relief and comfort to loved ones.

End of Life Eating Habits
As individuals approach the end of their life, their body undergoes significant changes, including a natural decline in appetite and nutritional needs. This phase is often characterized by a decreased desire for food and fluids, which can be distressing for families and caregivers.
Here are some of the most common changes we see with eating habits towards the end of life.
1. Loss of Appetite and Reduced Food Intake
As the body nears the end of life, metabolic processes slow down, and the need for energy diminishes. This often leads to a reduced desire to eat or drink. It’s important for families to understand that this is a normal part of the dying process and not a sign of suffering.
Loss of appetite happens because the body can no longer absorb or utilize food effectively, and the desire to eat naturally fades.Initially, individuals may prefer liquids or soft foods like broth, pudding, or yogurt, as these are easier to consume and digest.
Eventually, even these may be refused as the body’s need for sustenance continues to decrease. This preference is due to the body’s declining ability to process solid foods, which can become burdensome on the digestive system.
2. Weight Loss
Reduced food intake naturally leads to significant weight loss. This can be alarming for families, but it is a normal aspect of the body’s gradual shutdown. The body is not starving in the traditional sense; it is simply no longer able to utilize food effectively.
Weight loss at this stage is a result of decreased caloric intake and the body’s overall decline in function.
Along with overall weight loss, muscle wasting can occur as the body breaks down muscle tissue for energy. This can lead to weakness and fatigue, further reducing the individual’s ability to participate in daily activities
3. Difficulty Swallowing (Dysphagia)
Dysphagia, or difficulty swallowing, often develops as the muscles involved in swallowing weaken. This can lead to coughing, choking, or even aspiration, where food or liquid is inhaled into the lungs, increasing the risk of pneumonia and other complications.
Managing dysphagia involves offering small, manageable bites of food, and sometimes using thickened liquids to make swallowing easier.
As swallowing becomes more difficult, individuals may avoid solid foods altogether, preferring only liquids or very soft foods. This is a protective mechanism to prevent choking and discomfort.
4. Dehydration
Similar to food intake, the desire for fluids diminishes. Dehydration at this stage does not cause the same discomfort as it would in a healthy individual. Signs of dehydration include dry mouth, cracked lips, and decreased urine output.
It’s important to keep the mouth moist for comfort, using swabs or sips of water as tolerated.
While it might seem counterintuitive, reduced fluid intake can actually bring relief. For instance, it can decrease fluid buildup in the lungs, which reduces coughing and congestion. Less fluid means less swelling and potentially less pain from conditions like edema.
5. Changes in Taste and Smell
As the end of life approaches, changes in taste and smell can make food less appealing. Foods that were once favorites may no longer be desired, and even the smell of food can become unpleasant.
This is part of the body’s natural process of shutting down and can be a signal to caregivers to adjust the types and amounts of food offered.
Sometimes, individuals may become more sensitive to certain smells or flavors, finding them overpowering or unpleasant. Caregivers should be mindful of these changes and offer bland, easily digestible foods when possible.
6. Fatigue and Weakness
As the digestive system slows down, food and fluids can become more difficult to process, leading to symptoms such as nausea, vomiting, bloating, and abdominal discomfort. These symptoms are common and can be managed with medication and dietary adjustments. Offering small, frequent meals instead of larger ones can help reduce discomfort.
The digestive system’s reduced efficiency can cause food to sit in the stomach longer, leading to bloating and pain. Caregivers should be aware of these symptoms and provide supportive care as needed.
7. Gastrointestinal Symptoms
As the digestive system slows down, food and fluids can become more difficult to process, leading to symptoms such as nausea, vomiting, bloating, and abdominal discomfort. These symptoms are common and can be managed with medication and dietary adjustments. Offering small, frequent meals instead of larger ones can help reduce discomfort.
The digestive system’s reduced efficiency can cause food to sit in the stomach longer, leading to bloating and pain. Caregivers should be aware of these symptoms and provide supportive care as needed.
8. Changes in Bowel Movements
The body’s slowing down affects all systems, including the gastrointestinal tract. This can result in constipation, which may require stool softeners or laxatives, or diarrhea, which needs to be managed carefully to maintain comfort. Both conditions can be distressing and require careful management to ensure the patient’s comfort.
With reduced food intake, bowel movements naturally decrease in frequency and volume. This is a normal part of the body’s decline and should not be a cause for alarm.
9. Signs of Body Shutdown
As fluid intake decreases and the body’s functions decline, urine output will naturally diminish. This is a sign that the kidneys are no longer working as effectively, which is a normal part of the dying process. Caregivers should monitor for signs of discomfort and provide supportive care as needed.
Circulatory changes can lead to cold hands and feet as the body prioritizes blood flow to vital organs. This is often accompanied by mottling of the skin, particularly on the legs and arms, which indicates the body’s systems are slowing down. Providing warm blankets and ensuring a comfortable environment can help ease any discomfort.
Breathing may become irregular, with periods of rapid breaths followed by pauses (Cheyne-Stokes breathing). This is a normal part of the body’s final adjustments and should be managed with supportive care.
The Biggest Cue
All of the above cues largely result in reduced food and fluid intake that doesn’t meet their caloric daily requirements under normal circumstances. But as the body is going through the dying process and resting more, caloric requirements decrease.
The reduction in food and fluid intake is a natural response to the body’s changing needs. It’s important to recognize that this decrease is not akin to the hunger or thirst experienced by healthy individuals.
Instead, it’s a part of the body’s preparation for a peaceful and natural passing. Forcing food or fluids can lead to discomfort, including nausea, bloating, and respiratory issues, as the body is no longer equipped to process and utilize them effectively.
Nutritional Needs and Comfort Care
At this stage, the focus of care shifts from meeting nutrition goals to comfort measures. The aim is to ensure that the individual’s remaining time is as comfortable and dignified as possible.
This might mean offering small amounts of favorite foods or sips of water if they are desired, but also recognizing when to refrain from encouraging intake.
Understanding these changes in end of life nutrition helps caregivers and families navigate this challenging time with sensitivity and respect for their loved one’s natural journey. It emphasizes the importance of comfort and quality of life over conventional nutritional goals, aligning care practices with the individual’s end of life experience.
Common Concerns and Misconceptions
Navigating the end-of-life journey brings a myriad of emotions and questions, particularly regarding eating habits. It’s common for families and caregivers to grapple with concerns about their loved one’s decreased appetite and fluid intake.
Addressing these concerns requires dispelling some of the prevalent misconceptions about hunger and thirst at the end of life.
Misconception: “They are starving”
One of the most distressing thoughts for families is the idea that their loved one is starving. However the sensation of hunger typically diminishes as the body prepares for the end of life. This natural decrease in appetite means that the individual does not experience hunger in the way a healthy person might. The body’s reduced demand for energy results in a corresponding decrease in the need for food.
Misconception: “They are dehydrated”
Similarly, concerns about dehydration arise when fluid intake decreases. While hydration is vital for a healthy, active body, the needs change significantly during the end-of-life phase. The sensation of thirst diminishes, and the body may no longer process fluids effectively. Excessive fluid can lead to discomfort, including swelling, congestion, and increased risk of respiratory issues.
Misconception: “Artificial nutrition increases comfort”
Artificial nutrition at the end of life, such as feeding tubes or IV nutrition, is generally not recommended because it can often do more harm than good. As the body prepares for the end of life, its ability to process and use nutrients diminishes.
Introducing artificial nutrition can lead to discomfort, including bloating, nausea, and increased risk of infections. It may also extend the dying process without improving quality of life, potentially causing additional distress for both the patient and their loved ones.
The focus at this stage should be on comfort and quality of life, respecting the natural decline in the body’s need for food and fluids.
Understanding these aspects of end-of-life care helps to alleviate some of the guilt or worry families may feel about their loved one’s changed eating habits. It’s a time to prioritize comfort, presence, and emotional support, recognizing that these are the most valuable forms of care we can offer as someone prepares to leave this life.

Practical Tips for End of Life Nutrition
Caring for someone at the end of life is a profound and challenging experience, especially when it comes to managing changes in eating habits. Here are practical tips to someone at the end of life while respecting their changing needs and ensuring their comfort.
Offer Small, Frequent Meals
As appetites decrease, large meals can be overwhelming. Instead, offer small, frequent meals throughout the day. This approach is less daunting and allows the person to enjoy a variety of foods without feeling pressured to eat a lot at once.
Focus on Favourite Foods
Pay attention to the foods and drinks your loved one enjoys and try to incorporate them into their diet. This not only provides them with pleasure but can also evoke positive memories and emotions, enhancing their quality of life during this time.
Managing Symptoms That Affect Eating
Common symptoms like nausea, dry mouth, or difficulty swallowing can make eating challenging. Work with the hospice care team to manage these symptoms effectively. For example, keeping the mouth moist with ice chips or special mouthwashes can help with dryness, while anti-nausea medication can make eating more comfortable.
Create a Pleasant Eating Environment
Make mealtime as enjoyable and stress-free as possible. A calm, comfortable setting can help your loved one feel more relaxed and willing to eat. Playing soft music, using attractive dishes, and ensuring a comfortable seating arrangement can all contribute to a more positive dining experience.
Be Flexible with Meal Times
Listen to your loved one’s body and be flexible with meal times. They may feel more hungry or awake at different times of the day. Offering food when they’re most receptive ensures they get the nutrition they need without feeling forced.
Encourage Independence
Allow your loved one to eat independently if they’re able. This can help maintain their dignity and sense of control. Adaptive eating utensils and easy-to-handle foods can facilitate self-feeding.
Stay Hydrated
Hydration is important, but like with food, it’s essential to follow the loved one’s cues. Offer small sips of water, ice chips, or moist fruits to keep them comfortable. Avoid forcing large amounts of fluids, as this can lead to discomfort.
When Nutrition Interventions Stop Working
Accepting that nutrition interventions are no longer beneficial marks a pivotal moment in the care of individuals at the end of life. This realization typically comes when it’s clear that such interventions no longer contribute to the patient’s comfort or well-being, and may, in fact, detract from the quality of their remaining days.
Recognizing this requires careful observation and communication with healthcare providers, who can offer insight into the signs indicating that the body is naturally reducing its need for food and fluids as part of the dying process.
One key indicator is a persistent decline in appetite and interest in food, despite attempts at nutritional support. This change is often accompanied by the body’s decreased ability to digest and absorb nutrients, leading to discomfort and adverse effects such as nausea, bloating, or fluid overload.
When these signs become evident, it’s crucial to consult with the care team to reassess the goals of care, focusing on symptom management and quality of life rather than on sustaining or extending life through artificial means.
Accepting this shift in care priorities can be emotionally challenging for families and caregivers, who may view providing food and hydration as fundamental acts of care. However, transitioning to a comfort-focused approach—emphasizing pain relief, emotional support, and the alleviation of distressing symptoms—can offer a more peaceful and dignified end-of-life experience.
Open discussions with Dietitians, healthcare professionals, support groups, and spiritual advisors can provide valuable support during this time, helping caregivers make informed decisions that honour their loved one’s wishes and promote their comfort in the final stages of life.
Final Thoughts
Navigating the end-of-life journey with a loved one involves a delicate balance of care, compassion, and understanding, especially when it comes to changes in eating habits. This journey, while challenging, offers an opportunity for deep connection, reflection, and respect for the natural processes at the end of life.
Understanding that decreased appetite and fluid intake are part of the body’s preparation for passing allows caregivers and families to focus on what truly matters: providing comfort, love, and dignity to their loved one in their final days. By embracing the principles of hospice care, caregivers can ensure that their loved ones receive the most compassionate and appropriate support during this time.
It’s important to remember that every individual’s journey is unique, influenced by their personal, cultural, and spiritual beliefs. Respecting these differences and prioritizing the wishes of the individual ensures that care is not only respectful and dignified but also deeply meaningful.
The journey through the end of life is a profound experience for both the individual and their loved ones. By focusing on comfort, presence, and emotional support, caregivers can navigate this path with grace and love, creating a peaceful and respectful environment for their loved one’s final days.
Information For Dietitians
How long can you live without food and water in hospice care?
This is a tough question to answer for Dietitian’s. The true answer is that every person is going to last different periods of time. We as Dietitian’s cannot give a definitive timeline.
What we can say is that you should offer food and fluids under the following circumstances at end of life:
- The patient is awake and alert enough to safely feed
- The patient is not actively pushing away, pursing their lips, or refusing the food and fluids
- The patient is in an upright position to eat and drink
Food and fluid refusal is common towards the last days of life. If the patient is rejecting the food and fluids, we should respect this. This is difficult for a loved one to observe.
Studies 6 have shown that while loved ones have a hard time with a lack of intake, suffering is not increased in the dying patient. It’s KEY to provide this information to loved ones! If you haven’t checked out the blog on how to have this discussion, click here.
In summation, we can say that when food and water intake stop in a hospice patient, death is likely very close.
What is the End of Life Dehydration Process?
You more than likely will be approached by a family and asked for your thoughts on end of life hydration. You will want to provide the family education on the end of life hydration benefit or burden.
End of Life Hydration Benefit or Burden?
The organs during the dying process are shutting down. Body functions are slowing because the body only wants to maintain enough function to live. By offering excess amounts of hydration beyond what the body processes need, can cause discomfort.
The research currently tells us that end of life hydration is not beneficial in a dying patient. Research actually compared end of life hydration individuals to those who didn’t. The results showed no extension to life in those with end of life hydration.
We should provide loved ones with the education that research currently doesn’t support that rehydration will extend life or provide greater comfort. Instead, we want to provide fluids when accepted. When fluids are no longer accepted, loved ones can be provided with swabs to keep their mouths moist.
End of Life Artificial Nutrition
This is another question you will be asked, should we consider artificial nutrition? This is a big ethical question and I’d love to get into it.
First off, you should know the difference between enteral and parenteral nutrition. But if you don’t, I’ll give you the brief lowdown on both.
Parenteral Vs Enteral: End of Life Tube Feed
There are complications associated with both, but with TPN, there are more complications and risks.
I have yet to find any strong research that suggests tube feeding results in a longer life. The research instead points to the ethical dilemma that happens when tube feeding is selected.
When you have the conversation, should we start artificial nutrition, you are there to educate and inform the family. Here are some talking points:

Stopping the Feeding Tube Discussion
Discussing with a family stopping a feeding tube at end of life is an incredibly difficult decision to have. If you want tips on how to have this conversation, I discuss further in the eBook and webinar.
But here are some talking points from research that are very important:
- Won’t Extend Life
- Research at this point doesn’t support artificial nutrition extending life. Nutrition and hydration are essential to live – but at the end of life, the organs are shutting down and don’t need the energy that they used to.
- Can Cause More Discomfort
- With the body only supporting vital functions to stay alive (breathing, heart beating, limiting blood flow, etc). The digestive system takes a backseat. By pumping in artificial nutrition and hydration this can cause bloating and discomfort. The GI system isn’t ‘turned on’ as efficiently, and this can lead to the body working harder.
- Associated Complications Can Be Serious
- Enteral and Parenteral Nutrition are both invasive procedures. Anytime you are introducing foreign substances or opening areas of the body, you risk infection. Parenteral nutrition also requires blood tests to monitor labs.
- Discontinuation a Very Difficult Decision
- I’m going to get into this one further below, but this is a serious talking point!
- What Would the Patient Want?
- All the conversations need to come back to this. Having an honest discussion about what would the patient have wanted if they were able to make the choice now. It is obviously ideal if this is in the advanced care directive, but not all do.
What About Feeding Tube Removal?
I want to get into this a little bit more because I think it’s an important focus. Artificial nutrition at the end of life will wind up with a feeding tube removal discussion. Talking about feeding tube removal is tough, so approach with compassion.
Start the conversation EARLY and be honest on the pros and cons, like I discussed above. When I say start the conversion early, I mean AS SOON AS THE DOCTOR DECLARES THEM END OF LIFE!
I want to emphasise: Do not avoid telling them that if a tube feed is initiated, at some point feeding tube removal will be a discussion.
Research points to artificial nutrition being more of an ethical than clinical question for this exact reason. Families really need to be aware of the heavy impact and emotional distress that is associated with feeding tube removal.
It is easier to make the decision to keep a patient comfortable and hydrated as best we can, than to discontinue tube feeding. End of life is inevitable, the goal should be what the patient would have wanted.
So what should our focus be with end of life nutrition care?
Comfort Feeding at the End of Life
In all these discussions, we are not advocating that if we aren’t using artificial nutrition we’re advocating for no feeding. Research suggests that loved ones think that it’s either one or the other. Instead we’re focusing on supporting the individual with both their verbal and nonverbal cues if they want to eat.
I believe that the goal should be comfort feeding at the end of life. Comfort feeding is a combination of all of these factors below.
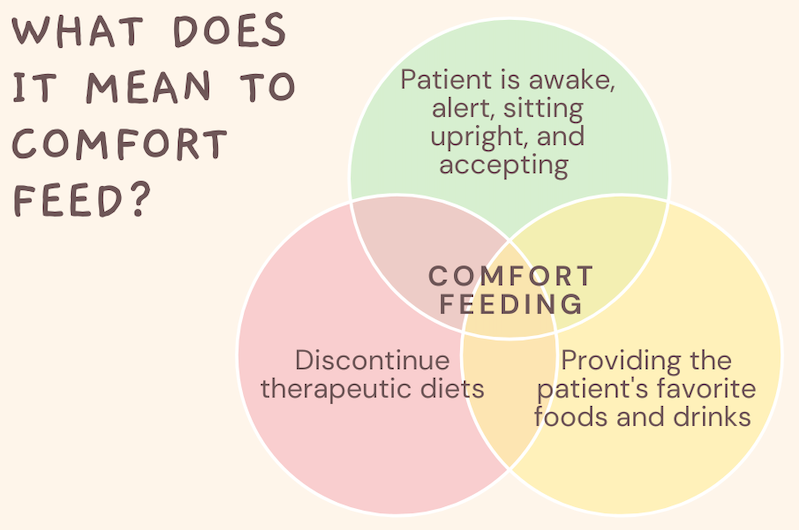
This sums up perfectly the focus that we should be going for with comfort feeding at the end of life.
The most important point out of all of this though is to start the discussion early! If the patient can be involved in the discussion, then it is easier for the family to accept their choice. Many will say that they do not want a feeding tube. But family’s won’t know unless they’re asked.

Michelle Saari is a Registered Dietitian based in Canada. She has a Master's Degree in Human Nutritional Sciences and is a passionate advocate for spreading easy to understand, reliable, and trustworthy nutrition information. She is currently a full time online entrepreneur with two nutrition focused websites.


What about when it comes to oral nutrition supplements? If they or family want a nutritional supplement(i.e Ensure) due to a varied or poor appetite, should we start one as long as resident continues to accept to help maintain nutritional intake/hydration/skin integrity/etc? Or should we try to shy away. Its so hard to tell if adding kcal/protein in form of supplements would be seen as okay or not. Are supplements always seen as unnecessary on hospice services?
Thank you.
Unfortunately there is no one answers fits all situations. Research shows that oral nutritional supplements do not extend nor improve quality of life when end of life is imminent. Giving someone too much fluids can actually increase discomfort as it’s making their body continually work when it is in all likelihood trying to slow down.
That being said, end of life can technically last 6 months, which in the scheme of things is quite a good amount of time. A big factor to consider here is easing the emotional burden that the family feels at this time. So while in theory we know that ONS don’t extend life, it can play a HUGE role in making the patient and family feel like a “good death” occurred. A “good death” is when the patient is treated with all comfort measures possibles at the end of life, and the family feels a significant sense of trust in the healthcare staff that they are doing everything they can to make the patient comfortable.
So if a family is requesting an ONS, I will have a discussion with them that it won’t necessarily extend life, but if the patient is not eating adequate amounts and will accept an ONS, I will absolutely sign off on them receiving it daily.
I know that is slightly confusing, but what textbooks say doesn’t always reflect what occurs in real life. We aren’t dealing in theory, we’re dealing with peoples real emotions, and real people. Quality of life needs to out weigh just about everything and at the end of the day, our job is to do what’s in the best interest of the patient and their loved ones. So take it on a case by case basis, but if it will bring a sense of peace to the loved ones, and the patient is happy to accept it, then certainly give an ONS on a regular basis. It may be much easier nutrition for them as opposed to eating food.
I just started my Masters in Applied Nutrition and our first assignment was to discuss the ethical issues of a patient who asks to stop tube feeding. I remember seeing you post this article in the RD FB community and I immediately came back to this to read. I found this deeply insightful and helpful, especially as this is a difficult topic! Thank you so much! <3
Thank you for the feedback, Franchesca! I’m so glad that you found the article helpful!
I have been working as a LTC dietitian for 9 months now and I love my job. This article is very useful as I’ve had residents go into hospice and some who eventually pass on, and had the difficult task of talking to family members and comforting them and the struggle with finding the right words or things to say. I would love to learn more…
Thanks for the comment, Anne! It can be incredibly difficult to start these conversations but you form such a fantastic connection with the loved ones and you can be a real benefit to their end of life journey. If you want to learn more I recommend looking at the ebook and course in the shop! You can find it here: End of Life Nutrition Conversation eBook & Course
Great info I was going g to share with the hospice nurses in my home health agency Where can I find the references mentioned in the text . Thanks
Hi Beth-Anne,
Thank you for the comment! You can see superscript numbers within the article and if you click each one, it will take you to the research article, or reference cited.